• Skip to primary navigation
  • Skip to main content
  • Skip to primary navigation
  • Skip to main content
Choose which site to search.
University of Arkansas for Medical Sciences Logo University of Arkansas for Medical Sciences
College of Medicine: Department of Family and Preventive Medicine
  • UAMS Health
  • Jobs
  • Giving
  • About Us
    • The DFPM Chair
    • Department News
    • Department of Family and Preventive Medicine Research Symposium
    • Department of Family and Preventive Medicine CARE Awards
    • Verification of Residency Training
    • Available Positions
  • Residency Programs
    • Family Medicine Residency Programs
    • Preventive Medicine Residency Program
  • Community Health and Education
    • Upcoming Events
    • CME/CE for Family Medicine
    • Partnerships in Colorectal Cancer Screening for Arkansas
      • Who We Are
      • Providers’ Resources for Colorectal Cancer Screening
      • Patient Resources
      • PiCS-AR! Raises the Bar
  • Research and Scholarly Activity
    • Clinical Research
    • Community Research
      • Research & Evaluation
        • Arkansas Early Childhood Care & Education Financing: Cost Modeling & Market Price Analysis
        • Arkansas Workforce Studies
        • Child & Youth Mental Health
        • Healthy Families America (HFA)
        • Home-Visiting Support for Low-Birth-Weight Preterm Infants
        • Parents as Teachers (PAT) Arkansas
      • Research-Based Early Childhood Professional Development
        • Engage Continuum
        • FIRST:ECE
        • TIPS
        • WOW
        • Family Map
        • Project PLAY
        • REACH
        • WISE
        • Strengthening Families
      • Research and Evaluation Division Faculty
        • Nikki Edge, Ph.D.
        • Lorraine McKelvey, Ph.D.
        • Taren M. Swindle, Ph.D.
        • Kanna Lewis, Ph.D.
      • Contact RED
    • Publications
  • Medical Student Education
    • Junior Clerkship
      • Clerkship FAQs
      • Clerkship Syllabus
      • Contacts
      • Community and Housing
    • Senior Students
      • Residency Resources and Timeline
      • Post Match Survey
      • Student Alumni Sign-up Form
    • Scholarships and Loan Repayment
      • Harold H. Hedges III, M.D., Endowed Scholarship in Family Medicine
    • Student Conferences
  • DFPM Offices
    • Communication and Departmental Relations
    • Digital Health
    • Leadership and Professional Development
      • DFPM Chair’s Awards for Recognition of Excellence (CARE)
        • Chair’s Awards for Recognition of Excellence Nomination Form
    • Wellness
      • DFPM/PCPHSL MVP Award Nomination Form
        • MVP of the Month Recipients
  1. University of Arkansas for Medical Sciences
  2. College of Medicine
  3. Department of Family and Preventive Medicine
  4. Community Health and Education
  5. Page 3

Community Health and Education

How We Keep Each Other Safe – Middle School

To view this lesson plan as PDF, click here. 

Objectives  

Students will:  

  • Explain why communities need trustworthy systems for reporting concerns.  
  • Evaluate the benefits and potential misconceptions about anonymous reporting.  
  • Analyze real-world examples of caring vs. harmful behavior, including digital scenarios.  
  • Reflect on personal values related to community safety.  

Materials  

  • Google Slides: Link 
  • Student Paper: Link
  • Whiteboard for group notes (If necessary)  

Lesson Activities  

Warm-Up: Think–Pair–Share   

  • Ask students to discuss: “What makes a community feel safe? What threatens that safety?”  
  • Record responses.  

Case Study Analysis   

Students work in small groups to review short scenarios. Students identify:  

  • Caring behaviors  
  • Harmful behaviors  
  • Actions that require adult intervention  
  • How anonymous reporting could help  

Mini-Lesson: Purpose of Anonymous Reporting   

Lead a brief lesson on:  

  • Why communities need safe reporting channels  
  • How anonymous reporting reduces fear of retaliation  
  • How reporting supports not punishment, but intervention and care  

Prompt:  

  • “How does anonymous reporting help protect the person you’re worried about?”  
  • “How does it help protect you?”  

Individual Reflection   

Journaling prompts:  

  • “What values guide my actions when I see something unsafe?”  
  • “Have I ever been unsure whether to report something? What made it difficult?”  
  • “How can anonymous reporting make a difference in real situations?”  

Discussion Prompts  

  • “Is reporting someone ‘snitching,’ or is it something else?”  
  • “What does caring look like in middle school friendships?”  
  • “What barriers stop students from speaking up?”  

Notice of Federal Funding and Federal Disclaimer

Filed Under: Community Health and Education

Scenario Sort – Middle School

To view this lesson plan as a PDF, click here. 

Objectives  

Students will:  

  • Analyze real‑world style scenarios to determine safe and appropriate responses.  
  • Understand the difference between anonymous reporting, trusted‑adult conversations, and non‑reportable events.  
  • Discuss the value of anonymity, including reducing peer pressure, stigma, and fear of retaliation.  

Materials  

  • Student Worksheet: Link

Learning Activities  

Introduction  

  • Ask students: “Think of a time someone needed help but didn’t feel comfortable asking. What made it hard?”  
  • Share a few voluntaries (optional, no personal details).  

Scenario Sort Activity  

  • In small groups or individually, have students complete the student worksheet that has them sort scenarios into anonymous reporting, trusted‑adult conversations, and non‑reportable events.  

Class Discussion  

Bring class back together. Discuss:  

  • “How do we decide when anonymity is important?”  
  • “Why might someone hesitate to report a serious concern?”  
  • “What’s the difference between “snitching” and supporting safety?”  
  • “What are the risks of NOT reporting?”  

Highlight anonymity benefits:  

  • Protecting the reporter  
  • Encouraging honesty  
  • Stopping harm early  

Optional Exit Ticket  

Have students complete one of the following sentence stems:  

  • “Anonymity is important because…”  
  • “One scenario that felt challenging to categorize was…”  
  • “One thing I learned about staying safe at school is…”  

Notice of Federal Funding and Federal Disclaimer

Filed Under: Community Health and Education

Helpful Reports – Middle School

To view this lesson plan as a PDF, click here. 

Objectives  

Students will:  

  • Learn what adults look for when reviewing a report.  
  • Distinguish between emotions and evidence-based details.  
  • Practice rewriting vague, dramatic, or incomplete reports into more helpful versions.  
  • Understand that the goal is support and safety, not punishment.  

Materials   

  • Mini-Lesson Google Slides: Link 
  • Student Paper: Link

Learning Activities  

Introduction  

  • In small groups, have students brainstorm answers to the following question: If you were reporting something anonymously, what information would you need to include?  
  • Bring class back together and share answers.   

Mini-Lesson  

Teach: A strong, appropriate report is:  

  • Clear (facts, not conclusions)  
  • Specific (details that help adults follow up)  
  • Respectful (no name-calling/slurs/judgments)  
  • Reliable (identifies what they saw/heard, not rumors)  

Provide appropriate examples and ask students what might be missing or not helpful about each example.   

Report Rewriting  

Give groups 4–6 sample anonymous reports with common issues:  

  • Overgeneralizing  
  • Emotional outbursts  
  • Missing key details  
  • Judgments instead of facts  
  • Rumors or “someone said that someone said…”  

Students provide missing information or rewrite to improve.   

Group Discussion  

Discuss:  

  • “How did you decide what details were important?”  
  • “What made a rewritten report more helpful and less emotional?”  
  • “Why shouldn’t we avoid reporting even if we’re unsure?”  

Notice of Federal Funding and Federal Disclaimer 

Filed Under: Community Health and Education

How We Keep Each Other Safe – High School

To view this lesson plan as a PDF, click here. 

Objectives 

Students will:  

  • Examine why communities require safe, confidential systems to address concerns.  
  • Understand the role of anonymous reporting in preventing harm and supporting wellbeing.  
  • Evaluate complex ethical situations involving safety, privacy, responsibility, and digital communication.  
  • Reflect on their values and responsibilities as members of a school community.  

Materials  

  • Student Paper: Link
  • Whiteboard for Whole Group Notes  

Lesson Activities  

Opening Reflection   

  • Ask students: “What is the difference between ‘getting someone in trouble’ and ‘getting someone help’?”  

Ethical Dilemmas Group Work   

Small groups analyze more complex scenarios.  

Groups answer:  

  • What harm is present or possible?  
  • Who is affected directly and indirectly?  
  • How could anonymous reporting support a safe outcome?  

Whole-Class Debrief   

Discuss themes:  

  • Fear of retaliation  
  • Loyalty vs. responsibility  
  • Safety culture  
  • Intervention vs. punishment  

Reinforce the idea: “Anonymous reporting is a tool for early support. It is not about punishment. It’s about care, prevention, and connecting people to resources.”  

Reflective Journaling  

Student Paper Written Prompt: 

  • “How can anonymous reporting empower students to protect each other?”   

Discussion Prompts:  

  • “Should safety ever outweigh privacy? When and why?”  
  • “How does digital communication change the risks and responsibilities of students?”  
  • “What kind of school culture makes reporting feel safe?”  
  • “What barriers might stop me or my peers from reporting concerns?”  

Notice of Federal Funding and Federal Disclaimer 

Filed Under: Community Health and Education

Helpful Reports – High School

To view this lesson plan as a PDF, click here. 

Objectives  

Students will:  

  • Understand how anonymous reports are evaluated for urgency and credibility.  
  • Analyze and correct vague, dramatic, or ambiguous reports.  
  • Practice creating reports that are concise, objective, respectful, and actionable.  
  • Reflect on ethical considerations: safety, privacy, bias, and appropriate use.  

Materials  

  • Mini-Lesson Google Slides: Link 
  • Student Paper: Link

Learning Activities  

Introduction  

  • Ask students: “What could happen if we don’t provide enough information in an anonymous report?”  

Mini-Lesson  

Explain that strong reports generally include:  

  • What you observed or heard (firsthand if possible)  
  • When it occurred (approx. time/date)  
  • Where it happened  
  • Why it concerns you  

Highlight respectful language and avoiding assumptions or diagnoses (“he’s crazy,” “she’s dangerous”).  

Provide anonymized, somewhat realistic samples. Students identify weaknesses such as:  

  • Emotional exaggeration  
  • Lack of detail  
  • Gossip/rumors  
  • Judgmental tone  

Report Rewriting  

With the student worksheet, give groups 4–6 sample anonymous reports with common issues:  

  • Overgeneralizing  
  • Emotional outbursts  
  • Missing key details  
  • Judgments instead of facts  
  • Rumors or “someone said that someone said…”  

Group Discussion  

Discuss:  

  • “Why is clarity important but not required for reporting?”  
  • “How do we avoid unintentionally shaming or labeling someone?”  
  • “Why is reporting still encouraged even if your description isn’t perfect?”  

Emphasize: It is always better to report than to stay silent. Adults can sort through details; students don’t need to investigate.  

Notice of Federal Funding and Federal Disclaimer 

Filed Under: Community Health and Education

Scenario Sort – High School

To view this lesson plan as a PDF, click here. 

Objectives  

Students will:  

  • Evaluate complex, nuanced safety‑related scenarios.  
  • Determine when an anonymous report is the safest, most ethical action.  
  • Explore issues of confidentiality, stigma, personal responsibility, and digital citizenship.  
  • Understand how anonymous reporting complements direct communication or adult involvement.  

Materials  

  • Student Paper: Link

Learning Activities  

Small Group Sort  

  • On student paper, have student sort scenario cards into anonymous reporting, trusted‑adult conversations, and non‑reportable events.  

Class Discussion  

Bring class back together. Discuss:  

  • “How do we balance someone’s privacy with the need to protect them?”  
  • “When is anonymous reporting the most responsible choice?”  
  • “What could happen if we misjudge a situation as ‘not serious’?”  

Emphasize: 

  • Anonymous reporting exists to prevent harm, protect bystanders, and support mental health.  
  • It is part of a larger safety system including adults, peers, and trusted communication.  

Optional Exit Ticket  

  • Have students answer the following question: “How will you decide in the future to decide if something should be reported anonymously?”  

Notice of Federal Funding and Federal Disclaimer 

Filed Under: Community Health and Education

Notice of Federal Funding and Federal Disclaimer 

This Web site is funded in whole or in part through a grant from the Bureau of Justice Assistance, Office of Justice Programs, U.S. Department of Justice. Neither the U.S. Department of Justice nor any of its components operate, control, are responsible for, or necessarily endorse, this Web site (including, without limitation, its content, technical infrastructure, and policies, and any services or tools provided).

Filed Under: Community Health and Education

How Early Screening Helps Primary Care Clinicians Uncover Youth Substance Use

Ninety percent of people addicted to substances started drugs before they were 18, and anxiety, depression and even suicide are often linked with addiction. That’s why early detection is crucial, said Caitlyn Johnson and Kim Shuler, licensed social workers with Arkansas Behavioral Health Integration Network.

They presented evidence-based adolescent substance use screening tools such as the SBIRT model (Screening, Brief Intervention and Referral to Treatment) at the UAMS 29th Annual Family Medicine Update Oct. 29, 2025.

The event was sponsored by the UAMS Department of Family and Preventive Medicine’s Community Health and Education division. Arkansas Children’s National Center for Opioid Research and Clinical Effectiveness sponsored the first day, “Opioids and the Young.”

Speakers Caitlyn Johnson and Kim Shuler, both social workers with the Arkansas Behavioral Health Integration Network
Caitlyn Johnson and Kim Shuler with Arkansas Behavioral Health Integration Network

Trends in Teen Substance Use: Alcohol Still Leads

The social workers surprised the primary care audience by revealing that alcohol trumps nicotine and THC as adolescents’ most used substance because it is readily accessible and culturally accepted. But the good news is that binge drinking is trending down, according to the National Institute on Drug Abuse, even though it’s still a contributor to 74% of premature deaths among teens.

“Substance use can contribute to feeling more uninhibited and having suicidal thoughts,” said Shuler. “Suicide is something that we need to have in the forefront of our minds.”

How SBIRT Works in Primary Care

“The key is to be as preventative as possible and provide education and tools for these teens,” Johnson added, referring to SBIRT, which stands for screening, brief intervention and referral to treatment. SBIRT screening tools often take five minutes or less to administer. Substance Abuse and Mental Health Services Administration (SAMHSA) recommends starting at age 12, but children as young as 10 are using substances

“Think about using universal screening for substances, meaning at every visit, use a screener. One of the things we know is that sometimes, when we’re asking someone (about their substance use), they may not tell us the first time. So, it’s important to continually bring this up,” said Shuler.


SBIRT - The 35,000 Foot View
Screening, Brief Intervention and Referral to Treatment (SBIRT) is one of the leading ways to reduce the impact of alcohol and substance use. Screening - Identifying adolescents who are at risk of negative consequences due to their substance use, including risk of a substance use disorder.
Brief Intervention - A conversation that is intended to either prevent, stop or reduce substance use disorder.
Referral to Treatment and Follow-up -- Linking the adolescent to substance use disorder treatment and other services, resources and supports and regularly checking in to facilitate sustained access.

The CRAFFT is one of the more common screening tools. There are others such as anxiety screener Generalized Anxiety Disorder, called GAD, and the PHQ-9A which screens for depression.

Whatever tool is chosen, it’s important to let the teen know that the provider is asking everyone about substance use and not singling them out. The provider must establish confidentiality, that the patient can be honest and trust them.

Clinicians should talk with the parent or caregiver first, conveying the importance of the screening and the need for confidentiality. This will settle the parent’s mind when asked if the teen can step out for a few minutes to speak privately.

Once that confidentiality is set, what if the young patient answers “yes” to any of the questions on the screener? Johnson said many providers feel they don’t have the tools to take the next step of intervention. One solution is to hire behavioral health consultants in the clinic, but providers have been hesitant to move to integrated care because of financial, training and space issues. Video on Arkansas providers who are taking the step toward behavioral health integration.

Brief Intervention Steps

teen boy talking to provider in office visit
Chances of developing an addiction are six times higher for teens who began using before age 15 than those who delay use until they’re 21.

Johnson and Shuler walked through the conversational steps for brief intervention when a behavioral health professional isn’t available.

If the CRAFFT screening score is low (0-2), the intervention may require only one to three minutes since the patient is low risk. If moderate to high risk, the intervention will take 15 – 30 minutes. Johnson said to allot enough time to complete the intervention.

“There are barriers to seeing the doctor, such as missing school and insurance being able to pay and things like that. So you want to make sure you give as much as you can in one session,” said Johnson. She added that the intervention can be extended to several sessions with either the provider or medical team. “If you run into an adolescent or young adult that is not ready to make behavior change, that is OK. That’s to be expected. Their brains are still developing, and they are learning how to make those educated decisions,” said Johnson.

The social workers covered a step-by-step example of brief intervention called the Brief Negotiated Interview model, created by the Boston University School of Public Health. It has six stages.

    1. Build engagement and rapport – Show interest in them as a person, the things they’re putting in their body and the risks. “Would it be OK if we spent a few minutes talking about your alcohol or drug use?” If “yes,” go to question two, but if the answer is “no,” offer to be available to talk if needed.
    2. Pros and Cons – Ask what is enjoyable about using the substance and what’s difficult. “What else comes to mind when you think about how using the drug may impact your life, goals or wellbeing?”
    3. Feedback – Ask if they mind some education or thoughts on the situation. If “yes,” share one or two facts and ask their thoughts. If “no,” emphasize autonomy by saying the patient knows what’s best for them regarding the drug use.
    4. Readiness Ruler – Gauge their motivation for change, whether it’s low on the scale or high, and what can be done about it. “If you were to place yourself on a scale of 1 – 10 regarding how important it feels to make any change in your use of the drug, where would you be?” If the answer is four or above, ask why they chose that number and not a lower one. If the answer is 1 – 3, probe with the question, “What would have to happen to feel like making a change?”
    5. Negotiate Action Plan – Formulate goals with them. “So, now that we’ve had a few minutes to talk, what would you like to do, if anything? Would it be OK if I share some options?” Have them write down their goals and next steps. Focus on one to two short-term goals with specific steps.
    6. Summarize and Thank – They took a chance on being vulnerable with the provider, which can be painful. Ask, “Is this what you agree we went over? How do you feel about these goals that we set?”

    Shuler noted that one powerful preface to a question is, “I’m curious,” because curiosity invites openness and doesn’t equal judgment.

    When to Refer for Substance Use Treatment

    If the brief intervention reveals a need for more intensive care, Johnson said the referral needs to be to a licensed substance use professional at a treatment facility. Cost, insurance, school or parents’ work schedule are some potential barriers.“It’s not going to be the smoothest process,” said Johnson, “but it is worth a try to see if we can overcome those barriers through conversations or connections to resources.”

    The Arkansas Department of Human Services Office of Substance Abuse and Mental Health oversees prevention, treatment and recovery programs in the state and can help locate providers by area.

    An educational video from Dr. Aaron Weiner on youth substance use and mental health.

    Kim Shuler, LCSW, has more than 20 years of experience in clinical practice and leadership within integrated behavioral health. As CEO of ABHIN and project director for several HRSA-funded initiatives, she leads statewide efforts to advance access and quality. She is a certified behavioral health consultant with expertise in workforce training, coalition-building and strategic planning.

    Caitlyn Johnson, LCSW, has 10 years of experience in integrated behavioral health, care coordination and medical social work. She earned her bachelor’s and master’s degrees in social work from the University of Arkansas at Little Rock and serves as a project manager on multiple grants for the Arkansas Behavioral Health Integration Network. Johnson specializes in program development, brief intervention, harm/stigma reduction and suicide prevention.

    Filed Under: Community Health and Education, News Tagged With: brief intervention for youth substance use in primary care, primary care screening for youth substance use, SBIRT, youth substance use

    Family Medicine Update Oct. 29 – 31 offers 12 hours of virtual content for primary care

    The 29th Annual Family Medicine Update: Fueling the Front Line will offer up to 12 hours of online continuing education Oct. 29 – 31 for primary care physicians, advanced practice registered nurses and registered nurses, pharmacists, physician associates, physical therapists, respiratory therapists, certified health educators, social workers and substance abuse counselors.

    The virtual annual conference compiles the latest advances impacting family medicine, with a bonus of flexible, on-demand viewing through November 28, 2025.

    The first day – Opioids and the Young – offers four hours of content for only $25. The Thursday and Friday two-hour blocks are $40 each.

    To register, visit this link.

    Day 1

    The first day is Opioids and the Young, sponsored by Arkansas Children’s National Center for Opioid Research and Clinical Effectiveness. The day will include a talk on opioid use disorder in moms and children with Shona Ray-Griffith, M.D., an associate professor in the UAMS Depts. of Psychiatry and Obstetrics and Gynecology, and mandated reporting laws with Jessica Coker, M.D., assistant professor in the UAMS Dept. of Psychiatry. Other topics include behavioral health screening and intervention for adolescents with Kim Shuler, LCSW, and Caitlyn Johnson, LCSW, both with the Arkansas Behavioral Health Integration Network. The last session will be “Opioids Off the Table? Now What?” with Teresa Hudson, Pharm.D., Ph.D., a professor in the UAMS Dept. of Psychiatry.

    Caitlyn Johnson and Kim Shuler, social workers
    Caitlyn Johnson and Kim Shuler

    Day 2

    Talks on the second day will feature UAMS providers: sniffles, chills and fever in kids with Rachel Ekdahl, M.D., and Satvika Mikkilineni, D.O.; “Naloxone Know-How for Saving Lives” with Leah Tobey-Moore, DPT, MBA, and Meghan Breckling, Pharm.D.; and a fresh look at hypertension medications with Michelle Hernandez, Pharm.D. Alexis White, M.D., also will speak on menopause.

    Alexis White, MD
    Alexis White, M.D.

    Day 3

    The last morning of the virtual conference will focus on cancer screening in Arkansas, presented by Daniele Ramirez-Aguilar, MPH, with the Arkansas Central Cancer Registry, and “Mending a Child’s Heart: Pediatric Cardiology from a Nurse Practitioner Perspective” with Leslie Lewis, APRN, who works at Children’s Medical Center in Dallas, Texas. The two afternoon sessions will feature Robert Hopkins Jr., M.D., who will update attendees on immunization essentials for the fall. He is the division director for the UAMS Dept. of Internal Medicine. Next will be “Spotlight on LADA: The Hybrid Diabetes of Adulthood” with Hadeel Al Fares, M.D., an endocrinology, diabetes and metabolism fellow at UAMS.

    Robert Hopkins Jr., M.D.

    Filed Under: Community Health and Education, News Tagged With: Family Medicine Update, Oct. 29-31, Virtual CME

    Family Medicine Conference Warns of Trend for Early-Onset Colorectal Cancer and Highlights Topics Important to Family Medicine

    Family medicine providers gathered for UAMS’ virtual 2025 Family Medicine Spring Review April 23 -25 and learned that the colorectal cancer death rate in people younger than 55 is climbing one percent each year since the mid-2000s, but that this group is more open to a yearly stool-based screening test such as the fecal immunochemical test (FIT) or Cologuard than other age groups.

    The colorectal cancer screenings updates from Whitney Jones, M.D., a gastroenterologist from Kentucky, and Francis Colangelo, M.D., a primary care physician with Allegheny Health Care in Pittsburgh, were part of the first day of the three-day conference.

    Francis Colangelo, M.D. talking with Family Medicine Spring Review logo on the side.
    Francis Colangelo, M.D., primary care physician, speaking on early-onset colorectal cancer.

    “Around 41 percent of these (younger patients) had symptoms for at least six months before visiting a provider,” said Colangelo. “And if you see rectal bleeding, always assume it is colorectal cancer in the younger patient.”

    The conference was presented by the Department of Family and Preventive Medicine’s Community Health and Education division, which has produced continuing medical education for 47 years.

    Amanda Deel, D.O., associate dean of the New York Institute of Technology’s College of Osteopathic Medicine, spoke on compassion in healthcare.

    “Following a compassion-centered script with patients may feel artificial, but in a study, patients didn’t sense that. Physicians miss opportunities to practice compassion 70 percent of the time and interrupt patients on average in the first 11 seconds,” said Deel.

    Angela Driskill, M.D.
    Angela Driskill, M.D.

    Angela Driskill, M.D., is a wound care specialist practicing at Baptist Health. She said there must be a distinction between pressure injuries and skin that fails because pressure injuries imply failure of care or harm.

    “If you don’t document a wound 12 to 24 hours after admission, it will throw up a red flag to CMS. Say it’s been 24 hours before anyone does a skin assessment, they are classified as ‘unwounded’ when they came in. Then we document there’s a stage 3 or 4 wound of the sacrum, and CMS begins to recoup the cost of that care, which can be $50,000 to $70,000,” said Driskill.

    Sleep medicine physician Caris Fitzgerald, M.D., offered trouble-shooting tips for patients who wear a CPAP, a machine that treats sleep apnea with continuous positive airway pressure. CPAP manufacturers estimate that more than eight million people wear a CPAP each night. One common complaint is dry mouth.

    Picture of Caris Fitzgerald, MD
    Caris Fitzgerald, M.D.

    “A leak makes or breaks the experience with a CPAP,” said Fitzgerald, who sees patients at the Central Arkansas Veterans Healthcare System. “If a patient complains of dryness, fix the leak, don’t just increase the humidity. The nose is a humidifier. If your pressure system is sealed well and the patient is nasal breathing, they will not need a humidifier.”

    My goal with patients is 10LPM unintended leak. 10LPM is generally a good goal for 95% Unintended Leak. Most under 10LPM can do without a humidifier which means a lot less cleaning and expense. And those with co-occurring good use have almost always resolved the complaints associated with OSA.

    In his talk on metabolic issues, James Tucker, M.D., bariatric surgeon with Arkansas Heart Hospital, said bariatric surgery is not a cure for disease of obesity but a treatment. Sleeve gastrectomy is the more common surgery where 50 to 70 percent of the stomach is removed.

    “With insulin-dependent patients who’ve had the surgery, 60 percent to 80 percent experience remission from the disease,” said Tucker.

    On the third day of the conference, Amy Grooms, M.D., with the UAMS Department of Psychiatry, spoke about using transcranial magnetic stimulation for patients with treatment-resistant depression. She said transcranial magnetic stimulation uses a magnetic pulse that stimulates the dorsolateral prefrontal cortex and rebalances it with the subgenual anterior cingulate cortex. Around 30 percent of patients who use this treatment have a standard response, but 18 percent of patients report that their depression is gone.

    Bill Fantegrossi, M.D.
    Bill Fantegrossi, M.D.

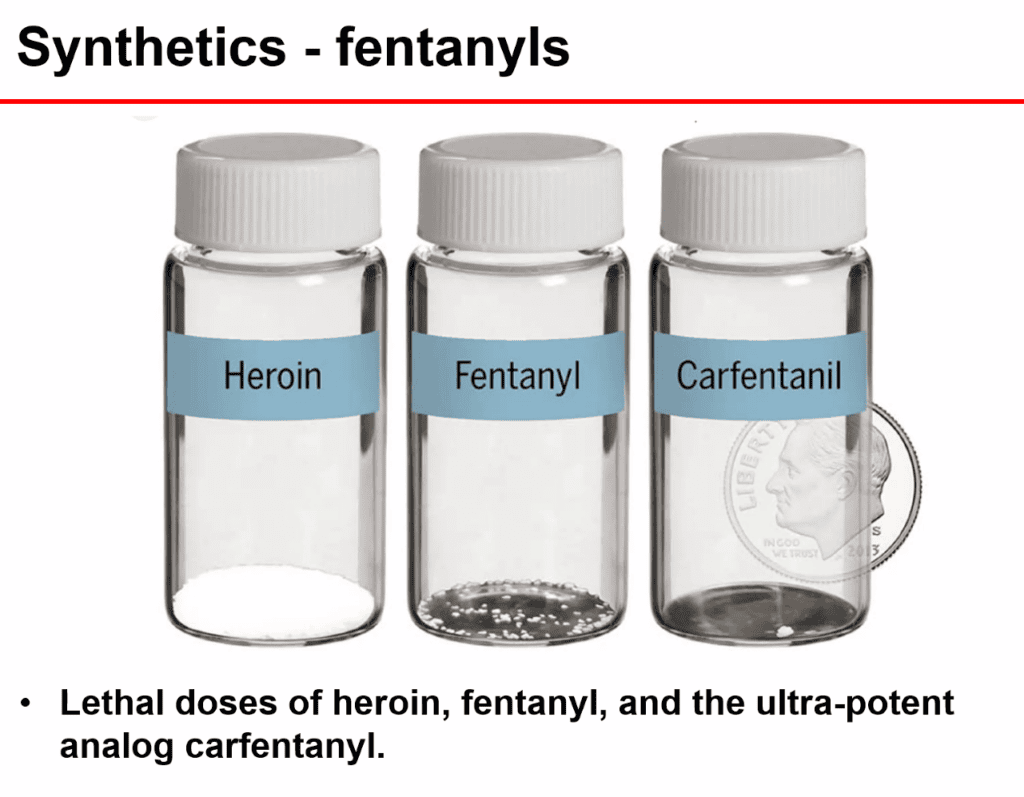
    Bill Fantegrossi, Ph.D, who works in the UAMS Department of Pharmacology and Toxicology, ended the conference with a talk on emerging drugs of abuse. He said new synthetic opioids grip more tightly to the opioid receptors in the brain. With such a strong bond, reversing an overdose is difficult with standard treatments such as naloxone (Narcan). Naloxone knocks opioids from brain receptors, but it struggles to unbind new synthetic opioids from receptors. This means it can only partially reverse an overdose or may fail.

    Synthetics - fentanyls. Lethal doses of heroin, fentanyl and the ultra-potent analog carfentanyl.

    Other conference topics included an update on the HPV vaccine with Portia Knowlton, who works with St. Jude’s HPV prevention program, renal cysts and masses with UAMS’ Marcelo Bigarella, M.D., and long-term effects after curative cancer treatments with Viriginia Laliberte, APRN. Ashley Acheson, Ph.D., and Jami Jones, who work with the National Center for Opioid Research & Clinical Effectiveness at Arkansas Children’s Hospital, spoke on the research they are conducting on children and adolescents who have been affected by the opioid crisis and other drug addictions.

    Filed Under: Community Health and Education Tagged With: bariatric surgery, cancer, CME virtual conference, colon, CPAP, emerging drugs of abuse, screening, skin failure

    • «Previous Page
    • Page 1
    • Page 2
    • Page 3
    • Page 4
    • Next Page»
    UAMS College of Medicine LogoUAMS College of MedicineUniversity of Arkansas for Medical Sciences
    Mailing Address: 4301 West Markham Street, Little Rock, AR 72205
    Phone: (501) 686-7000
    • Facebook
    • X
    • Instagram
    • YouTube
    • LinkedIn
    • Pinterest
    • Disclaimer
    • Terms of Use
    • Privacy Statement
    • Legal Notices

    © 2026 University of Arkansas for Medical Sciences